Module 1: Introduction to Birth Doula Work — 8 Hours
Topics Covered:
Definition of a birth doula
The history and evolution of doula work
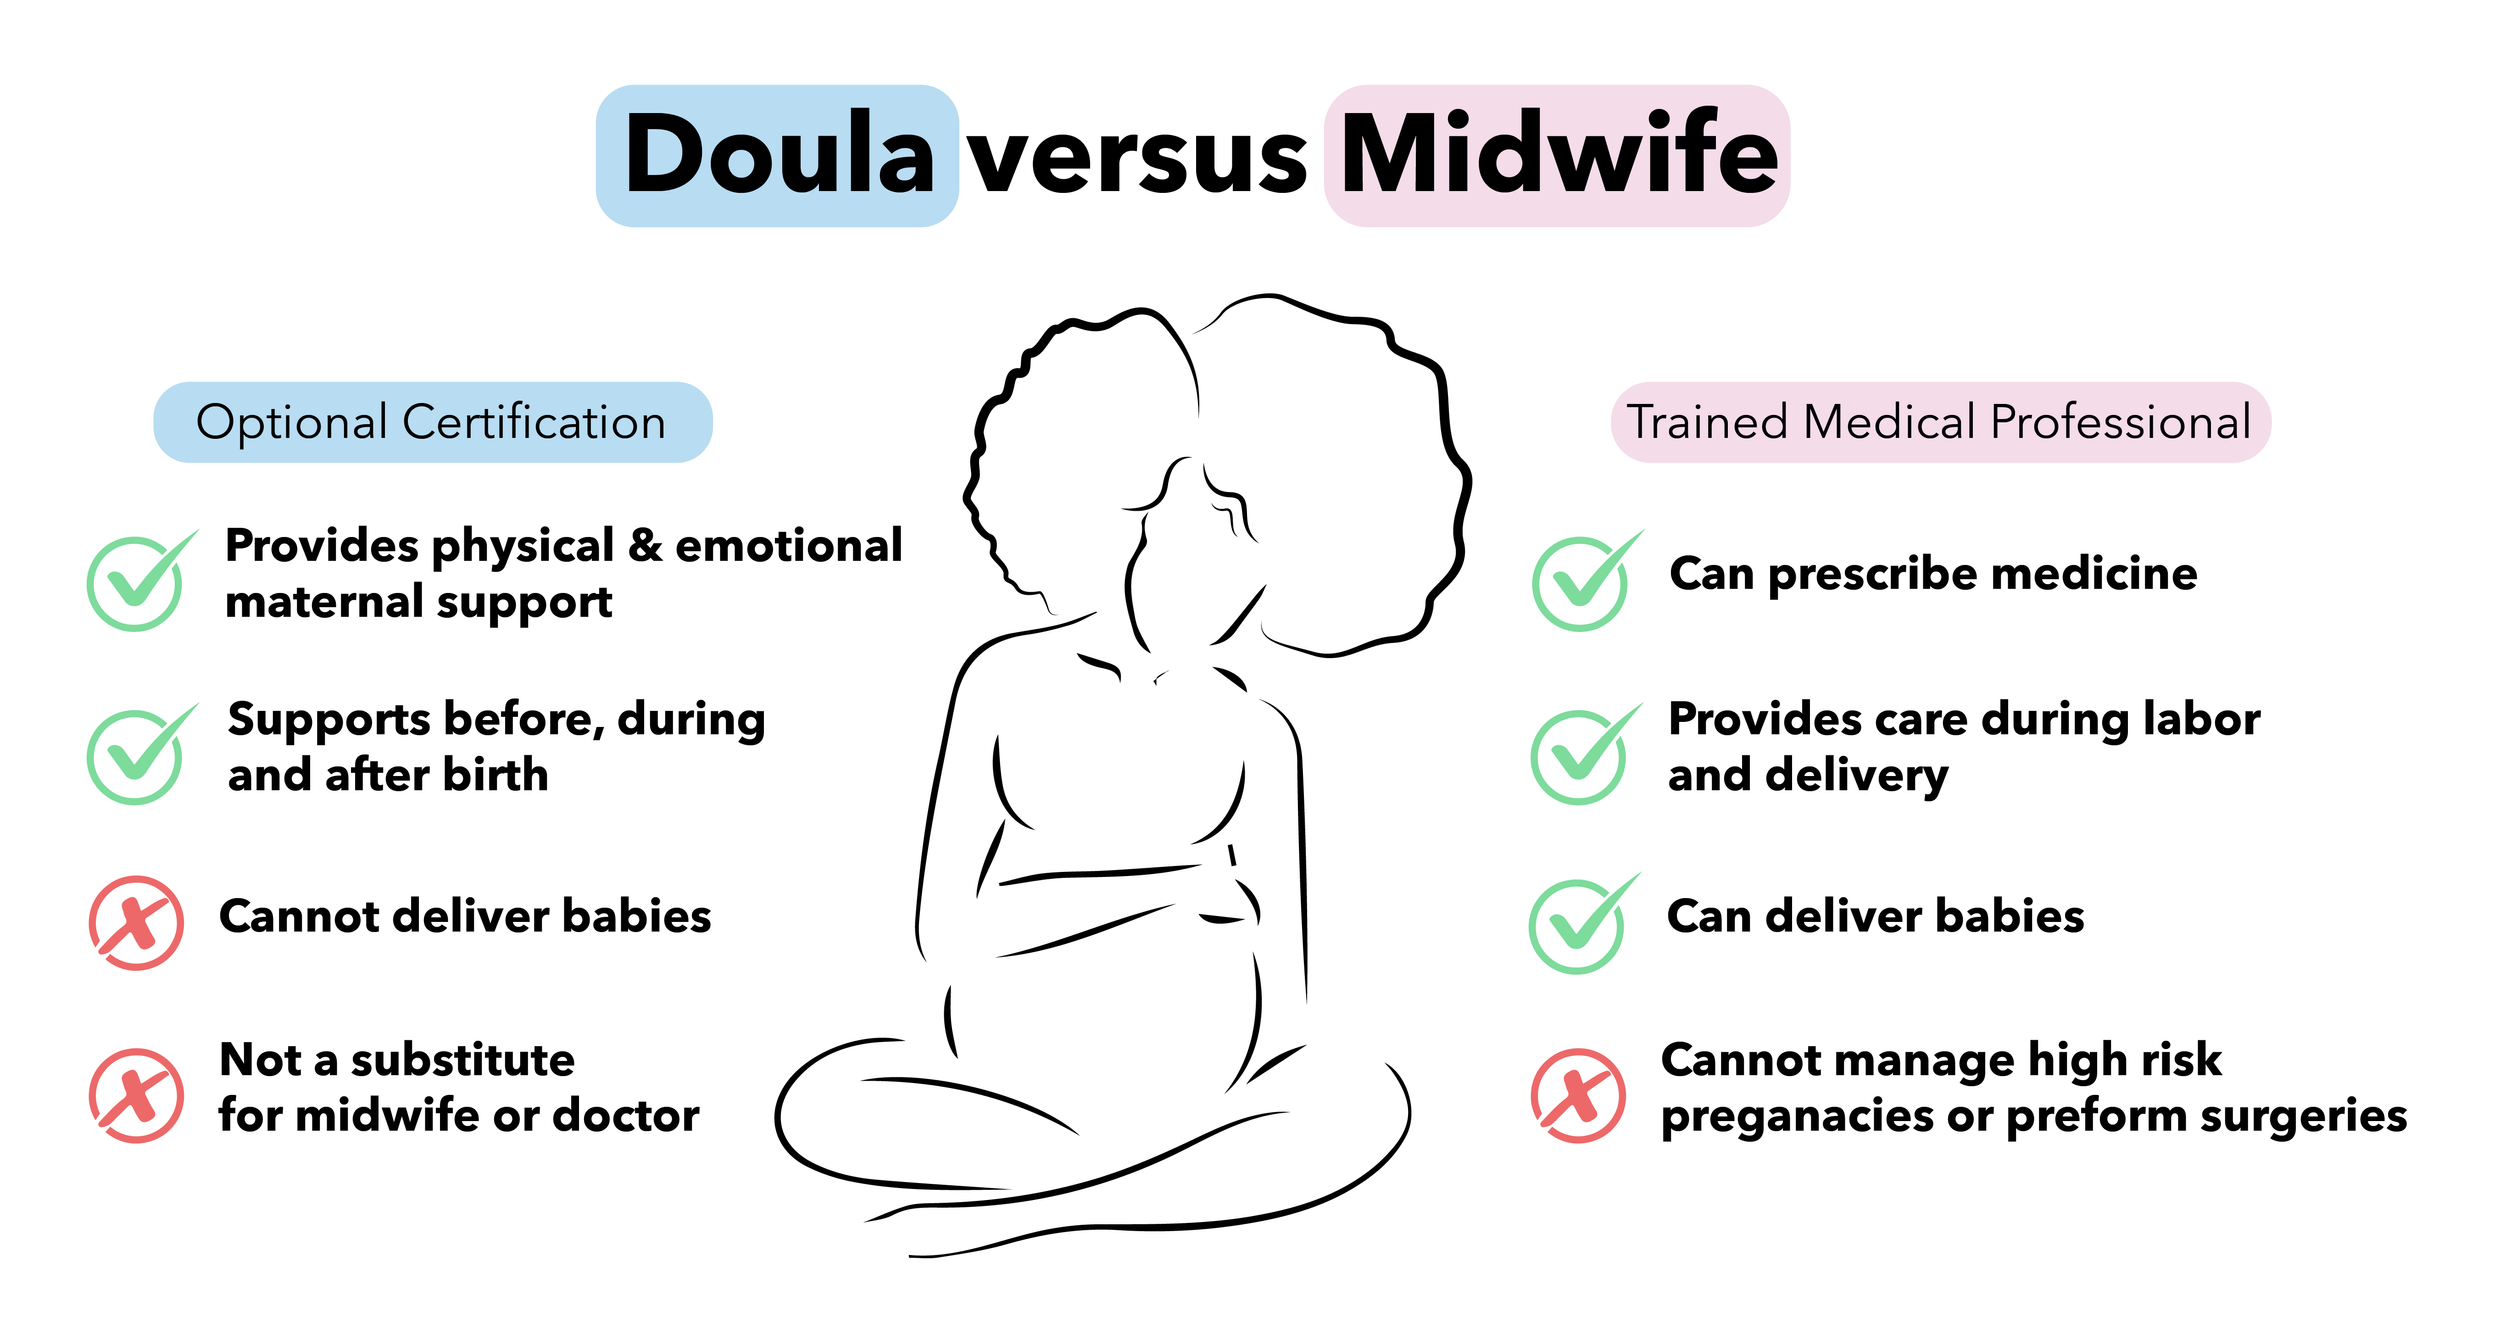
Distinguishing between a doula, midwife, and other birth professionals
IN THIS LESSON

Introduction
When families prepare for birth, it’s natural to have questions about who will be by their side and what roles each professional plays. While doctors and midwives provide essential medical care, doulas offer something different but equally important: continuous emotional, physical, and informational support. In this lesson, we’ll explore exactly what a birth doula is, trace the history and evolution of doula work, and clarify how doulas differ from midwives, nurses, and other professionals. By the end, you’ll understand how each role fits together to create a supportive birth team.

Unit 1 · Lesson 1
Definition of a Birth Doula
Who we are, what we do, and where our role begins and ends
Learning objectives
- Say what a birth doula is, and describe the role through pregnancy, labor, and the first hours after birth.
- Explain the three pillars of doula support (emotional, informational, and physical) and give an example of each.
- Tell the difference between a birth doula and medical providers such as nurses, midwives, and doctors.
- Practice with five activities: a history timeline, a branching case, a role-play script builder, a myth vs. fact game, and a flashcard deck.

Where does the word "doula" even come from?
Before you say what a doula does, it helps to know where the word comes from. The history tells you a lot about the job.
The word doula comes from ancient Greek: δούλα. It means "woman servant" or "woman who serves." A medical anthropologist (someone who studies people and health) named Dana Raphael was the first to use it in this modern way. She wrote about it in her 1973 book The Tender Gift: Breastfeeding, which grew out of her dissertation (a long research paper for a PhD). She used the word for a supportive woman who helps a new mother after the baby is born, especially with breastfeeding. Raphael was the first scholar to use the word for a childbirth helper.
The word caught on for birth work in the 1980s. Two doctors who were also researchers, Marshall Klaus and John Kennell, began major clinical trials (studies that test something in real patients). They wanted to know what happens when a woman has steady support during labor. Their work, along with Phyllis Klaus, Penny Simkin, and Annie Kennedy, helped turn the doula role into a real profession. The research they started is still growing today.
Think about being sick. A friend who stays beside you all day is a different kind of help from a friend who stops by once an hour. That difference is what these researchers were studying.
Why this helps: Dates are easier to remember as a story. When you see how the word and the research grew, you can explain to a client or her family where doula care comes from.
Tap any date to open the story and see where it came from.
Why the word matters
Here, "service" doesn't mean being someone's servant. Think of a skilled guide who serves a traveler by helping them get where they want to go. A doula serves the birthing person's experience, wishes, and sense of safety. She does not serve the hospital, the clock, or anyone else's plan. For example, if your client wants a quiet room with dim lights, you help make that happen. It's her birth, not yours. So the word itself works like a compass for the role.
How the research defines the role
You don't need to rely on any one group's definition. Across dozens of studies, clinical reviews, and meta-analyses (which combine the results of many studies into one), researchers describe the birth doula in almost the same words. Here are three examples:
"A doula is a trained maternal support professional who offers emotional, informational and/or psycho-social care during pregnancy, childbirth and/or the postpartum periods. Doulas do not replace but complement the role of clinicians (physicians, midwives and nurses)."— Patient-Centered Outcomes Research Institute (PCORI) systematic review, 2023
"Doulas are trained, non-medical providers who provide emotional, informational, and physical support during pregnancy, labor, and the postpartum period."— Kozhimannil et al., qualitative study on community doula implementation, PMC, 2024
"Doulas are non-medical childbirth companions [who] provide emotional, informational, physical, and advocacy support to people during pregnancy, birth, and postpartum."— Springer Nature: Maternal and Child Health Journal, 2025
In plain English: a doula is trained, is not a medical provider, and gives emotional, informational, and physical support. A doula works alongside the medical team, not against it.
All three quotes agree on the same points: non-medical, trained, steady presence, three kinds of support (emotional, physical, informational), and a team relationship with clinical providers. These aren't sales talking points. They're the definition researchers have reached over decades. Let's look at three key words.
Trained. A doula is not just a kind friend who happens to be in the room. Training teaches how labor works in the body, comfort techniques, communication skills, and professional ethics. How deep the training goes depends on the certifying group. But researchers keep pointing to "trained" as a key detail. Studies that compare trained doulas with untrained support people show clearly stronger results for the trained doulas (Bohren et al., 2017). Think of a friend who cheers loudly at a race, compared with a coach who knows how to pace you.
Non-medical. This isn't a weakness. It's what makes the role work. A doula has no medical duties, so she can focus on the birthing person's feelings and comfort. She doesn't work shifts, juggle other patients, or fill out charts (Hodnett et al., 2013). Picture the nurse typing notes at the computer. The doula's hands and eyes are still on the client.
Continuous. This is one of the most important words in the research. A doula stays from the start of active labor, through the birth, and into the first hours after. She stays the whole time. We'll look at why that matters later in this lesson.

The three pillars of doula support
Doula support falls into three connected areas. Research keeps naming the same three (Hodnett et al., 2013; Bohren et al., 2017; Sobczak et al., 2023; Ramey-Collier et al., 2023):
❤ Emotional
Being there the whole time, reassuring, encouraging, making room for fear and joy, supporting partners, and building trust before and during labor.
🤲 Physical
Comfort measures: massage, firm pressure on the lower back (the sacrum, the flat bone at the base of the spine), help with positions, heat or cold packs, help moving around, and reminders to drink water.
📚 Informational
Explaining what's happening in labor, helping clients think of questions for their providers, going over birth preferences, and turning medical words into plain language.
Some research adds a fourth piece, advocacy (Hodnett et al., 2013; Springer Nature, 2025). It gets its own section below, because it's the part people misunderstand most.
Seeing all three pillars at once
Imagine your client is 7 cm dilated. (That means her cervix, the opening of the uterus, has opened 7 centimeters. Pushing usually starts at 10.) She starts to doubt herself and says, "I can't do this anymore." Emotional support: you move close, make eye contact, and say, "You are doing it. You're in transition, and that means you're almost there." Physical support: during the next contraction, you press firmly on her lower back. Informational support: you explain that transition, the hardest phase, is also the shortest. All of this happens in about three minutes. Researchers describe this layered approach as the mark of trained doula care (Bohren et al., 2017).
The scope of the doula relationship: before, during, and after
Prenatal (before birth)
Most doulas meet with clients two or three times during pregnancy. These visits do several jobs. You build trust. You learn what your client values and worries about. You go over her birth preferences. You teach the stages of labor. And you show the support partner how they can help. Morton and Clift (2014) call this relationship the foundation, meaning everything else is built on it. The trust you build before labor shapes how well you can help once labor starts.
Why prenatal visits matter so much
Picture two doulas arriving at the same birth center at 3 a.m. The first has met the laboring person twice. She knows the client is afraid of losing control, that pressure on the lower back helps her most, and that her partner goes quiet when anxious. The second doula is meeting the family for the first time. They have the same skills, but the first doula will be far more helpful. That's why prenatal visits aren't just paperwork. They are real doula work.
Intrapartum (during labor and birth)
This is the heart of birth doula work. The doula stays with the client from the time she's called, through the birth, and into the first stretch of recovery. Gilliland (2010) describes the emotional support doulas use in labor. It includes reflective listening (saying back what you heard so she feels understood), encouragement, mirroring (matching her rhythm and breathing), and "protecting an atmosphere of quiet focus." Physical support is just as specific: positions that ease pain or help labor move along, breathing, firm pressure on the lower back, and heat or cold (Gilliland, as cited in Bohren & Tunçalp, 2018). For instance, if she's tired of lying down, you might help her lean over a birth ball while you press on her lower back.
Postpartum (shortly after birth)
Most birth doulas stay one to two hours after the baby is born. They help with first bonding and early feeding. Many check in again within the first week to talk through the birth and share referrals (names of helpful resources, like a lactation consultant). Research says that working through how the birth felt, however it went, is a real need. Doulas are well placed to help with it (Sobczak et al., 2023). For example, a mother whose birth didn't go as planned may just need someone to say, "Tell me how it was for you." This is different from postpartum doula work, which is its own specialty and focuses on the weeks after birth.

What a doula is not: knowing the boundaries
Researchers agree on this point. A doula does not do clinical or medical tasks. She does not diagnose (name an illness or problem), prescribe (order medicine), or make medical decisions for the client (Hodnett et al., 2013; PCORI, 2023; Ramey-Collier et al., 2023). This isn't just a rule on paper. It's what makes the doula role possible. Because she isn't a clinician, she can stay with the client the whole time and keep her focus on how the birthing person is doing. For example, a doula never says, "Your baby's heartbeat sounds fine." That is the nurse's or midwife's job.
When clinical training and doula work overlap
Some doulas are also nurses or midwives. Here is the rule for them: if you are working as a doula, you cannot use your clinical skills at that birth. Research and scope-of-practice guides agree on this. The role is defined by the service you give, not by your background. The rule protects the client, the care team, and you. It prevents role confusion, which research links to conflict between professions (Bohren & Tunçalp, 2018). For example, a nurse working as a doula does not take her client's blood pressure, even though she knows how.
The easiest way to see the difference is a side-by-side comparison:
| Domain | Birth Doula | Nurse (labor & delivery) | Midwife / OB |
|---|---|---|---|
| Clinical assessments | No. Does not check dilation, listen to the baby's heartbeat, or do exams | Yes. Full monitoring and assessment | Yes. Full clinical scope |
| Medications / IV | No. Cannot give or recommend medications | Yes. Gives them under orders | Yes. Can prescribe and give them |
| Continuous presence | Yes. Stays with the client through the entire labor | Limited. Shared between patients, monitoring duties, and charting | Limited. Arrives for active or late labor and the birth |
| Emotional support | Core role. Main focus | Important, but second to clinical duties | Valued, but not the main role |
| Speaks for client | No. Helps communication and strengthens the client's voice, but never replaces it | Advocates within the clinical role | Advocates within the clinical role |
| Decision-making | No. Helps the client get information; the client makes all decisions | Informs and documents decisions | Makes clinical recommendations |
| Relationship start | Prenatal, weeks or months before birth | Start of the assigned shift | Built in prenatal care, or on-call |
One study found that nurses on labor and delivery units spend only 6–10% of their time on labor support. The reasons are charting, staffing limits, and caring for several patients at once. But birthing people expect nurses to spend about 53% of their time on support (Tumblin & Simkin, 2001; Gagnon et al., 1997, as cited in Ballen & Fulcher, 2006). This isn't a criticism of nurses. It simply shows why a separate role for continuous support is needed.
Watch
What is a doula? (Hennepin Healthcare)
Scenario to consider
Your client's nurse has just said she needs to stay in bed for continuous monitoring. (That means a belt around her belly tracks the baby's heartbeat the whole time.) Your client is upset. She asks you, "Can I just ignore that? You said I could move around."
A doula doesn't argue with the nurse, make the medical call, or push her own views about birth. Instead, you might say: "That's a really important question. Let's ask the nurse together why monitoring is needed right now, and whether there's any flexibility in how you can be positioned. You have every right to understand what's happening and to ask questions." You are the bridge, not the decision-maker. This is how the research describes the advocacy role (Bohren & Tunçalp, 2018; Hodnett et al., 2013).
Advocacy: the most misunderstood part of the role
The word "advocacy" gets a lot of attention in doula research, and some criticism. A 2018 paper in Health Expectations (Jenkinson et al.) looked at the ethical problems around how advocacy is defined and practiced. ("Ethical" means about right and wrong.) The authors noted that some training programs teach an "active advocacy" style. That style can slide into making decisions for clients, or challenging providers in ways that cause conflict.
The authors suggest basing the doula's role on relational autonomy. That's a big phrase from bioethics (the study of ethical questions in health care). It means people make choices as part of their relationships and surroundings, not alone. Fear, family, and the hospital setting all shape what we decide. So a doula doesn't speak for the client. She helps the client feel safe enough, informed enough, and supported enough to make her own choices and say them out loud.
"Grounding the definition of the doula's role in relational autonomy gives coherence and guidance to the work doulas do and has the potential to resolve the kinds of conflicts and misunderstandings that have been reported."— Jenkinson, Josey & Flemmer, Health Expectations, 2018 (PMC5810740)
In practice, advocacy means helping clients figure out and voice their own wishes. It means encouraging them to ask questions and supporting them to talk with their care team calmly and with good information. The goal is always to make the client's voice louder, not to take its place. For example, say your client told you, "I don't want to be induced," and then goes quiet when the doctor walks in. You might whisper, "Do you want to share what you told me?" You don't speak up for her.
The interpreter analogy
Think of yourself as an interpreter in a very important conversation. A good interpreter doesn't change the message, add opinions, or argue for one side. They make sure the meaning gets across clearly in both directions. That's your role in the birth room. The words belong to your client. Your job is to help her find and use them, even when she's in pain and under stress.
What the evidence says: why this role matters
Knowing the definition is easier when you know the research behind the role. This isn't a wellness trend. Doula support is among the most carefully studied non-pharmacological (non-drug) approaches in perinatal care, which is care around pregnancy and birth.
Bohren et al. (2017) — Cochrane systematic review
Continuous Support for Women During Childbirth combined the results of 27 randomized controlled trials. (In a randomized trial, people are put into groups by chance, so the groups can be compared fairly.) The trials included nearly 16,000 women in 17 countries. Women with continuous support in labor were more likely to have a spontaneous vaginal birth (a vaginal birth without tools or surgery) and shorter labors. They were less likely to use pain medication, to have an instrumental birth (using forceps or a vacuum) or a cesarean birth, or to have a baby with a low five-minute Apgar score. (The Apgar score is a quick health check of a newborn.) The review found no evidence of harm in any outcome it looked at. The effects were biggest when the support came from a trained person in a dedicated doula role, not hospital staff and not someone from the woman's own circle. (Bohren, Hofmeyr, Sakala, Fukuzawa & Cuthbert, Cochrane Database Syst Rev. 2017;7:CD003766.)
Collins et al. (2024) — American Journal of Public Health
This study looked at 722 matched pairs of Medicaid enrollees. (Medicaid is the U.S. public health insurance for people with lower incomes. "Matched pairs" means each person with a doula was compared with a similar person without one.) People with doula support had a 47% lower risk of cesarean delivery and a 29% lower risk of preterm birth, which means a baby born too early. They were also 46% more likely to go to a postpartum check-up. The researchers concluded that doula care is linked to better health outcomes among Medicaid enrollees. (Am J Public Health. 2024;114(11):1275–1285.)
Ramey-Collier et al. (2023) — Obstetrical & Gynecological Survey
This PubMed literature review looked at 34 original and review articles. It found that doula support is linked to more vaginal births and fewer preterm and low birth weight babies. The authors called it "a promising strategy to reduce healthcare inequities," meaning unfair gaps in care between groups. The effects looked especially strong for Black patients. (Obstet Gynecol Surv. 2023;78(2):124–127.)
Why presence itself is the intervention
Imagine running a marathon with a pace coach who runs every mile beside you. Now imagine one who checks in at miles 5, 13, and 26. Both care about you. But only one is there when you hit the wall at mile 18. That's the difference between a doula and support that comes and goes. Labor, like a marathon, doesn't pause while help is somewhere else. The Cochrane review points the same way: its biggest effects came from continuous support by a trained person.
A quick summary: what doulas do and don't do
- Stay with the client without a break, from active labor through the first hours after birth
- Offer physical comfort: massage, positions, heat or cold, and help moving
- Give emotional support, reassurance, and encouragement all through labor
- Share evidence-based, non-medical information with clients and partners
- Help clients think of questions and share their preferences with the care team
- Help the birth partner feel confident and useful
- Make talking with clinical providers easier, instead of leading the conversation
- Do clinical exams or assessments of any kind
- Give or recommend medications
- Make medical decisions or give medical advice
- Speak instead of the client or override her decisions
- Replace the midwife, nurse, or doctor
- Do clinical tasks, even if you're trained to do them in another job
Why this helps: Quick recall practice helps the definition, the key numbers, and your boundaries stick. Then you can say them calmly when a family asks.
Read the question, answer it in your head, then flip the card.
🧠 Check your understanding
1
In your own words, explain the difference between advocacy and decision-making in a doula's role. How does relational autonomy (Jenkinson et al., 2018) help make that difference clear?
2
A client in labor asks you, "Do you think I should get the epidural?" How would you answer? Use all three pillars of support and the idea that she makes her own informed decision.
3
A labor and delivery nurse tells a client's family, "The doula is basically just here to cheer her on." How would you explain the doula's role clearly and politely? What research could you mention?
4
The Bohren et al. (2017) Cochrane review found the best results when support came from someone in a "doula role," not hospital staff or a family member. Why do you think that matters? Which features of the doula role could explain it?
Peer-reviewed references
- Bohren, M. A., Hofmeyr, G. J., Sakala, C., Fukuzawa, R. K., & Cuthbert, A. (2017). Continuous support for women during childbirth. Cochrane Database of Systematic Reviews, 7, CD003766. https://doi.org/10.1002/14651858.CD003766.pub6
- Collins, C., Bai, R., Brown, P., Bronson, C. L., & Farmer, C. (2024). Role of doulas in improving maternal health and health equity among Medicaid enrollees, 2014–2023. American Journal of Public Health, 114(11), 1275–1285. https://doi.org/10.2105/AJPH.2024.307805
- Jenkinson, B., Josey, N., & Flemmer, M. C. (2018). Defining the doula's role: Fostering relational autonomy. Health Expectations, 21(1), 130–139. https://doi.org/10.1111/hex.12604 [PMC5810740]
- Ramey-Collier, K., Jackson, M., Malloy, A., McMillan, C., Scraders-Pyatt, A., & Wheeler, S. M. (2023). Doula care: A review of outcomes and impact on birth experience. Obstetrical & Gynecological Survey, 78(2), 124–127. https://doi.org/10.1097/OGX.0000000000001103
- Sobczak, A., Taylor, L., Solomon, S., Ho, J., Kemper, S., Phillips, B., … & Jacobs, R. J. (2023). The effect of doulas on maternal and birth outcomes: A scoping review. Cureus, 15(5), e39451. https://doi.org/10.7759/cureus.39451 [PMC10292163]
- Hodnett, E. D., Gates, S., Hofmeyr, G. J., & Sakala, C. (2013). Continuous support for women during childbirth. Cochrane Database of Systematic Reviews, 7, CD003766. https://doi.org/10.1002/14651858.CD003766.pub5
- Patient-Centered Outcomes Research Institute. (2023). Impact of doula support during pregnancy, childbirth and beyond: A systematic review. https://www.pcori.org/research-results/2023/impact-doula-support-during-pregnancy-childbirth-and-beyond-systematic-review
- Al-Adeli, N., et al. (2025). Role of doulas across the pregnancy care continuum on maternal and child health: A scoping review. npj Women's Health. https://doi.org/10.1038/s44294-025-00109-4
- Raphael, D. (1973). The tender gift: Breastfeeding. Prentice-Hall. [First scholarly use of the term "doula"]
- Morton, C. H., & Clift, E. (2014). Birth ambassadors: Doulas and the re-emergence of woman-supported birth in America. Praeclarus Press.
A Day in the Life of a Doula at NewYork-Presbyterian Brooklyn Methodist Hospital
A group of women in NYC is fighting to make doulas accessible to everyone
Featured Study

Gruber, K. J., Cupito, S. H., & Dobson, C. F. (2013). Impact of Doulas on Healthy Birth Outcomes.
Gruber, K. J., Cupito, S. H., & Dobson, C. F. (2013). Impact of doulas on healthy birth outcomes. PMC3647727. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3647727/
Summary:
This study compared pregnant people who had a certified doula with those who did not, while all participants were in a prenatal education program. Those with doulas were four times less likely to have a low-birth-weight baby and twice as likely to avoid a birth complication. They were also significantly more likely to initiate breastfeeding. The doula helped by providing continuous presence, physical comfort, and emotional encouragement throughout pregnancy and birth. Doulas assisted in guiding communication between the birthing person and clinical caregivers. The research suggests this one-on-one support contributed to better experiences and outcomes. Although counseling and case support were also provided to all participants, the additional doula presence correlated with measurable positive differences.
What It Means to Birth Doulas:
For doulas, this research highlights the value of continuous support—an element central to doula work. It shows how non-medical assistance (comfort, presence, information) relates to key birth outcomes like birth weight and breastfeeding. The study supports the idea that doulas help build confidence and agency in birthing people. It also underscores the role doulas play before labor, not just during labor. This helps doulas advocate for earlier engagement in prenatal care. For doula programs, the findings justify emphasizing holistic support strategies. Clinically, it provides evidence that doula care can complement medical care, especially for socially disadvantaged clients.
Translating for Doula Clients:
When talking with clients, emphasize how continuous support makes a meaningful difference:“Research shows that having a doula is linked with fewer birth complications and a greater chance of successful breastfeeding. I’ll be with you through pregnancy, labor, and early postpartum so you feel empowered and understood.”
You can also tie outcomes to comfort and confidence:“Studies find people with doulas build better communication with their care team and feel more in control of their birth.”
This helps normalize doula support as evidence-based. Reinforce that your role is supportive, complementary, and focused on their goals. Invite questions about preferences in care to build trust.

Unit 1 · Lesson 2
The history and evolution of doula work
From ancient birth rooms to modern hospital suites: the story hasn't changed as much as you'd think
Learning objectives
- Trace where doulas and traditional birth attendants came from, and what they did in different cultures.
- Understand how the modern doula profession grew and became recognized in today's maternity care.
- Name the social, cultural, and medical changes that shaped the doula role over time.
- Practice and check what you've learned with these activities: a process simulation, a myth vs. fact game, a role-play script builder, a branching case, and a skills checklist.
Birth support is ancient. The job title is new.
Let's start with a surprise: doulas are not a trend. People who give birth have needed steady, caring, non-medical support for as long as there have been people. In almost every culture we know of, women did not give birth alone in a clinical room. Experienced women from the community stayed close. They might have been grandmothers, neighbors, or older helpers. Their job was not to catch the baby. Their job was to hold the space around the person giving birth. That means they stayed calm, stayed present, and made her feel safe.
Here's what we know from history. Archaeologists have found stone carvings and old artwork that show women helping other women in labor. Ancient Egyptian texts describe skilled helpers at births. The ancient Greeks had a word for a woman who served, and that's where our word comes from. Doúla in Greek meant "woman who serves." In 1973, a medical anthropologist (a scientist who studies people and health) named Dana Raphael used the word for this modern role in her book The Tender Gift: Breastfeeding. She was the first scholar to put a name on something that had been happening for thousands of years.
Worth sitting with
The job is much older than the word. Say you meet a client whose family has strong birth traditions. You aren't offering her something foreign. You're offering a trained, modern version of what her great-great-grandmother probably already knew. Think of it like a family recipe that now has a written cookbook.
Three eras of birth support
It helps to see the story in three big chapters. Read the cards below, then use the simulation later in this lesson to feel the difference between them.
Before 1900s
Community-centered birth
Birth happened at home, with experienced women close by. Support came from people who knew her and shared her culture. It lasted the whole labor. Nobody changed shifts, and nobody had other patients to run to.
Early to mid 1900s
The medicalization gap
Birth moved into hospitals. More mothers and babies survived. But the steady, personal support went away. Families were often kept out. Many people labored alone or saw staff only now and then.
1980s to today
The evidence-based revival
Research showed what grandmothers had always known: having someone with you through labor helps. The professional doula was born. It's old wisdom in a new form.
What happened in the middle: the medicalization gap
"Medicalization" just means birth became a medical event, handled in hospitals by doctors and nurses. By the early 1900s, most birth had moved out of the home and into the hospital. That was a real medical win. Far fewer mothers and babies died, because hospitals had clean rooms and skilled doctors. Nobody should wish for the risks of birth in the old days.
But something got lost along the way. The steady, personal support that had always surrounded birth was left behind. Hospitals ran on shifts. Each nurse cared for several patients at once. Family members often waited in a different room. So the person giving birth, in one of the biggest moments of her life, was more alone than her mother or grandmother had ever been. That missing piece is what we call the "gap."
To picture it
Imagine you're starting something huge, physically and emotionally. People walk in and out every few hours. Nobody knows your name well. Nobody knows what scares you or what you hoped your birth would feel like. Now imagine your own mother never had that problem, because three women she'd known for years were beside her the whole time. For decades, the "alone" version was the normal one. The modern doula is there to close that gap.
Why this helps: Seeing the three eras side by side shows why one steady, familiar person matters. You'll be able to explain the "gap" with a picture, not just a definition.
Pick an era. Then drag the slider through a 12-hour labor. Watch who is with the birthing person, and whether anyone there knows her.
Green = someone who knows her is with her. Orange = only staff she has just met. Outlined = the hour you picked.
Who is with her
Knows her hopes and fears?
Staff handoffs so far
This is a simple teaching model based on the lesson's description of each era. The pattern of a new nurse every few hours is simplified. It isn't data from any one hospital.

Watch
How doulas can help deliver better birthing outcomes (Scripps News)
The research that changed everything
In the 1970s and 1980s, two doctors, Dr. John Kennell and Dr. Marshall Klaus, asked a simple question. Does it make a real difference if one steady person stays with a woman through labor? They studied it. The results stood out. Women with continuous support had shorter labors, fewer medical interventions (things like drugs or procedures to speed up or assist birth), and better feelings about their birth (Hodnett et al., 2013).
Later, researchers checked the question again on a much bigger scale. A "systematic review" is a study that gathers many smaller studies and looks at the results together. In 2017, the Cochrane review (Bohren et al.) did this with 27 randomized controlled trials. Those are studies where people are randomly placed into groups, which keeps the comparison fair. Together they covered nearly 16,000 women. The finding matched the earlier work: continuous support from a trained doula worked better than other kinds of support, or no support at all.
"Continuous labor support is a rare example of a healthcare practice found to have many benefits and no known harms."— Bohren et al., Cochrane Database of Systematic Reviews, 2017
In plain words: very few things in health care are helpful and also have no known downside. Steady support is one of them. This research gave the doula profession a solid science base and a reason to grow. Communities had done this by instinct for generations. Now there was strong evidence behind it.
How DNT Network fits into this story
Where you come in
The Doulas and Nurturing Traditions Network (DNT Network) was built on one idea. Honoring birth traditions from many cultures and using modern evidence are not two competing goals. They are the same goal. The name shows it: nurturing traditions is the ancient part, and network is the modern support system. DNT Network's training is open to people around the world. It is recognized by Medicaid programs and insurance providers. It was designed by public health PhDs, OB/GYNs, and certified midwives. That makes evidence-based doula education available across all 50 states and over 100 countries.
When you finish this training, you won't be starting a brand-new job. You'll be joining a very old one, with better tools, stronger proof, and a professional community behind you. That's the whole story in three steps: an ancient practice, science that backs it up, and a professional structure that supports you.
Scenarios & tips
Here are three real-life moments you're likely to face. Read each sample answer out loud. It should sound like something you'd actually say.
Scenario 1
A pregnant client asks why she should hire a doula when the hospital already has nurses.
"That's a great question. Nurses are very good at clinical care. But they're also watching monitors, writing notes, and often caring for more than one patient. My job is different. I'm with you from start to finish. I focus on keeping you comfortable, supported, and clear on your options. We're really a team."
Tip: This answer respects the nurses instead of competing with them. That's honest, and it builds trust with the hospital staff you'll work next to. Think of how a good coach talks about the referee: with respect, not a fight.
Scenario 2
A client from a culture with traditional birth attendants mentions that her grandmother was a "birth helper" at home.
"That's a beautiful tradition. In so many cultures, women have always helped each other through birth. That wisdom is real and it matters. What I do carries it forward in a modern setting. I want to honor those traditions and also help you find your way in the hospital, so you feel supported in both worlds."
Tip: Never say that professional doula work is better than cultural traditions. Say it continues them. This builds trust right away. You might also ask, "What did your grandmother do for women in labor?" and just listen.
Scenario 3
A partner asks if doulas are just a "new trend."
"Actually, doulas are about as old as childbirth itself. What's new is the training and the professional recognition. For thousands of years, every culture had experienced women who supported births. In the 1900s, birth moved to hospitals, and that community support got left behind. Doulas help bring it back, in a way that works inside modern health care."
Tip: Show that doula work has deep roots, so it doesn't sound like a wellness fad. This works especially well with doubtful partners or relatives. Keep your voice friendly, not defensive.
Why this helps: Practicing real questions out loud before a client asks them helps you answer calmly, without getting defensive or putting nurses down.
Why this helps: Checking only what you can say out loud, without notes, shows you the gaps. Then you know exactly what to review before the next lesson.
Check each statement only if you could do it out loud, without notes, with a client or a family member.
🧠 Check your understanding
1
What was lost when birth moved from home to hospital in the early 1900s? Why didn't nurses simply fill that gap?
2
How did Klaus and Kennell's research in the 1970s and 80s change how people thought about birth support? What did it prove that communities had always known by instinct?
3
The name DNT Network includes the words "nurturing traditions." Based on what you've read, why is honoring cultural birth traditions part of evidence-based doula work, and not separate from it?
References
- Bohren, M. A., Hofmeyr, G. J., Sakala, C., Fukuzawa, R. K., & Cuthbert, A. (2017). Continuous support for women during childbirth. Cochrane Database of Systematic Reviews, 7, CD003766. https://doi.org/10.1002/14651858.CD003766.pub6
- Hodnett, E. D., Gates, S., Hofmeyr, G. J., & Sakala, C. (2013). Continuous support for women during childbirth. Cochrane Database of Systematic Reviews, 7, CD003766. https://doi.org/10.1002/14651858.CD003766.pub5
- Raphael, D. (1973). The tender gift: Breastfeeding. Prentice-Hall. [First scholarly use of the term "doula"]
- DNT Network. (n.d.). About DNT Network. https://www.dntnetwork.com/about
- Morton, C. H., & Clift, E. (2014). Birth ambassadors: Doulas and the re-emergence of woman-supported birth in America. Praeclarus Press.
What is a doula?
Featured Study

The Effect of Doulas on Maternal & Birth Outcomes (2023)
The effect of doulas on maternal and birth outcomes: A scoping review. (2023). PMC10292163. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10292163/
Summary:
This scoping review looked across many studies to understand how doulas influence birth outcomes. It found that doula support is associated with fewer cesareans, shorter labor, and better breastfeeding success. Emotional support from doulas was linked to reduced stress and anxiety during childbirth. The review noted that doulas often help women feel more confident making decisions. Particularly for low-income women, doula involvement improved early breastfeeding and birth experience. The review suggests doulas may help close gaps in birth equity. It also acknowledged that access barriers exist and more research is needed to explore long-term maternal health.
What It Means to Birth Doulas:
For childbirth professionals, this review compiles consistent evidence that doula presence correlates with better physiological and emotional outcomes. It supports doulas’ role as a key part of person-centered support rather than an optional extra. The findings affirm doulas’ contributions to both physical and emotional well-being during birth. It also highlights the impact doulas can have for underserved communities. This reinforces the importance of culturally competent care. Doulas may be especially effective when incorporated early into prenatal planning. The data can help doulas demonstrate value to clients and care teams alike.
Translating for Doula Clients:
“Multiple studies show that continuous support through a doula is linked with less need for medical interventions and more satisfying birth experiences.”
Share evidence about emotional well-being: “Feeling calm and supported during labor isn’t just about comfort – research connects this support with positive outcomes like successful breastfeeding.”
Use language that validates their feelings and choices. Encourage them to think about the type of support they want. Reassure them that your work is rooted in research about maternal empowerment and resilience.
Unit 1 · Lesson 3
Distinguishing between a doula, midwife, and other birth professionals
Same room, very different jobs. Knowing the difference makes you better at yours.
Learning objectives
- Tell apart the jobs of doulas, midwives, obstetricians, and nurses during childbirth.
- Understand which tasks are non-clinical (no hands-on medical care) and which are clinical (hands-on medical care).
- See how doulas and medical providers working together can help families.
- Practice the vocabulary, the order of a good response, and your own readiness with interactive activities.

Everyone is on the same team, playing different positions
Picture a birth room. A nurse is checking the monitor. A midwife is looking at how labor is going. An OB-GYN (a doctor who delivers babies and handles problems) is on call down the hall. A partner is holding a hand. And there's a doula.
To someone walking in, it may look like everyone is doing the same thing: helping a person through labor. But each person has a different job. Knowing where your job starts and stops is one of the most useful things you'll learn as a birth doula.
Here's a simple example. Your client Maria is 38 weeks pregnant. Her mom visits and asks, "So which one of you is going to deliver the baby?" If you can answer calmly in one sentence ("The midwife will, and I'll be beside Maria the whole time"), everyone relaxes.
This matters for more than your own clarity. Research shows that mix-ups about who does what are one of the main causes of tension in birth settings (Wójcik-Brylska et al., Midwifery, 2023). When you know exactly what you do, and what you don't do, you work better with others, you stay safer, and people trust you more.
A useful way to picture it
Think of the birth team like an orchestra. The OB-GYN is the conductor, who steps in for tricky moments and makes the big calls. The midwife is the lead musician, trained to guide a normal birth. The nurse is a skilled section player, keeping many instruments going at once. The doula is the person who stays right next to the performer the whole time, so she feels supported enough to do what she came to do.
Meet the birth team
Two words will come up a lot, so here they are in plain English. Clinical means hands-on medical care, like checking vital signs or giving medicine. Non-clinical means no medical tasks. Doulas are non-clinical. The other three roles below are clinical.
Non-clinical
Birth doula
Gives steady emotional, physical, and information support from early labor through the first hours after birth. Does not do medical tasks. Stays for the whole birth, not just a shift.
Main focus: presence, comfort, communication
Licensed clinical
Certified nurse-midwife (CNM)
A licensed health professional who cares for low-risk pregnancies (pregnancies with no major health concerns) before, during, and after birth. Can listen to the baby's heartbeat, give medicines, and deliver babies. Works in hospitals, birth centers, and homes.
Main focus: medical care for normal births
Physician
Obstetrician / OB-GYN
A medical doctor who specializes in pregnancy, birth, and women's reproductive health. Cares for high-risk pregnancies (those with more health concerns), does cesarean sections (surgical births), and handles emergencies. Often arrives for the delivery or when a problem comes up.
Main focus: medical and surgical care
Licensed clinical
Labor & delivery nurse
A registered nurse who checks vital signs (like blood pressure and pulse), gives medicines, and helps the care team during labor. Often cares for several patients in one shift. Research shows nurses spend only 6–10% of their time on direct labor support (Al-Adeli et al., 2025). That's roughly 4 to 6 minutes out of every hour. It isn't because they don't care. They have many other tasks.
Main focus: medical monitoring and procedures

Why this helps: Mixed-up words lead to mixed-up roles. Learning these nine terms now means you can use them correctly with families and hospital staff.
Side-by-side: who does what
Use this table as a quick map. Read across a row to see who does each job. For example, find "Administers medications" (gives medicine). Only the clinical roles say Yes. Now find "Continuous presence." Only the doula says Yes.
| Task / responsibility | Doula | Midwife | OB-GYN | L&D Nurse |
|---|---|---|---|---|
| Continuous presence during labor | Yes | No — comes and goes | No — on call | No — works shifts |
| Delivers babies | No | Yes | Yes | No (except emergencies) |
| Administers medications | No | Yes | Yes | Yes (under orders) |
| Performs clinical exams | No | Yes | Yes | Yes |
| Cesarean sections | No | No | Yes | No |
| Emotional & comfort support | Yes — primary role | Yes — secondary | Yes — limited | Yes — limited |
| Prenatal relationship-building | Yes — weeks before | Yes | Yes | No |
| Makes medical decisions | No — never | Yes | Yes | Under supervision |
Look at the doula column again. Most rows say No. That can feel like a lot of "can't." But the one row with a Yes, continuous presence, is the heart of the job. The next section explains why.
Why the doula's non-clinical status is a superpower
It's easy to hear "non-clinical" and think it means "less than." It doesn't. A doula has no medical tasks, no charting, no other patients, and no medical decisions to make. That frees you to do something nobody else in the room can do: stay fully focused on one person for the whole labor.
Picture a nurse with three patients. Her attention gets pulled away when a monitor beeps in another room. That's not a flaw. It's the job. A doula's attention doesn't get pulled away.
Research backs this up. A big 2017 Cochrane review (Bohren et al.) pulled together the results of many studies on continuous support in labor. (A Cochrane review is a careful summary of many studies, so you get the big picture.) It found that results were best when the support came from someone who was there only to give support. That means not a staff member with medical duties, and not a family member. The doula is the only birth role defined by leaving out medical tasks. That is a big reason the role works.
Research: doulas and midwives together
A 2022 study in eClinicalMedicine (a journal from The Lancet) looked at doula programs in three U.S. states. It found that women who had a doula along with a midwife-led care team had the most steady drops in cesarean births (C-sections), no matter when doula care began. Overall, women with doula support had 52.9% lower odds of a cesarean birth and 57.5% lower odds of postpartum depression or anxiety. "Lower odds" means those outcomes were less likely. These results don't show doulas and midwives competing. They show the two roles work better together. (Falconi et al., eClinicalMedicine, 2022)

The collaboration challenge, and how to handle it
When doulas and midwives or nurses work well together, it can feel like a "team for the mother." That's the phrase used in a qualitative study from Oxford, England (McLeish & Redshaw, Midwifery, 2018). A qualitative study is one where researchers listen to people's experiences instead of counting numbers. In that study, doulas were seen as helpful colleagues who added to the care midwives could give. When things did not go well, mixed-up roles and unclear boundaries caused friction.
A review of many studies on doulas and midwives working together (Wójcik-Brylska et al., Midwifery, 2023) reached a clear conclusion. Good teamwork needs each person to understand the others' roles. Doulas who explain their purpose clearly and stay in their lane are much more likely to be welcomed by clinical staff.
Here's what that looks like in real life. When you meet a new nurse, you might say, "Hi, I'm Dana, Maria's doula. I'm here for comfort and support. I won't do anything medical. Just tell me if I'm in the way." That takes ten seconds and sets a friendly tone.
Watch
NMC and Doula UK discuss the differing roles of a midwife and a doula (NMCvideos)
Where tension tends to start
Research points to three common trouble spots. First, a doula seems to disagree with medical advice. Second, a doula "speaks for" the client instead of helping her speak for herself. Third, it's unclear what the doula is there to do. The fix for all three is the same: be clear, be humble, and work as a team. You're not there to compete with anyone. You're there to fill a gap that everyone else, because of their other duties, can't fill.
For example, say your client tells you, "I don't want that exam." Don't announce it to the nurse for her. Ask her softly, "Would you like to tell her yourself? I'm right here with you."
"The doula will be the only person who is consistent. That is so valuable because she can bond with that person, and the doula can help her feel safe and supported."— Certified nurse-midwife, quoted in Exploring Innovative Models of Doula Services, PMC, 2024
Scenarios & tips
Scenario 1
A labor and delivery nurse seems annoyed that you're there. She says, "We've got it covered in here."
"Absolutely. You're doing a great job handling everything. I'm here to give her steady emotional and physical support, so that doesn't fall on you. If there's anything I can do to help the room run smoothly, just tell me."
Tip: Nurses are often stretched thin, and some don't know what a doula does. Show that you see their workload, and show that your job helps theirs. That usually changes the mood fast. For example, a nurse with four patients may relax once she hears you'll handle back rubs and water refills.
Scenario 2
Your client asks whether she should accept the epidural (pain medicine given through a small tube in the back) that her midwife is suggesting.
"That's completely your decision, and I'll support you whatever you choose. Would it help to ask the midwife a few questions first? You could ask about timing and what other options you have right now. I'll stay right here while you talk it through."
Tip: This isn't your call, medically or personally. Your job is to help her feel informed and confident, not to push her one way. Offering to help her talk with the midwife is the right move. If you have strong feelings about epidurals, keep them to yourself in the room.
Scenario 3
A family member asks why their loved one hired a doula when she already has a midwife and a great hospital team.
"Great question. The midwife and nurses are very skilled. They take care of the medical side of birth. My job is different. I stay by her side the whole time, and I focus only on her comfort, her feelings, and making sure she feels heard. They work on the medical part, and I work on the human part. It works best when both are there."
Tip: Never say you're there to replace a weak medical team or make up for one. Say you add a layer of support that medical roles can't give because of their workload, even when they're excellent.
Why this helps: A good response has an order: respect first, then your role, then help. Practicing the order makes it easier to remember when you feel nervous.
Drag by the handle, or use the up and down buttons. Then press Check order.
Why this helps: Reading something is not the same as being able to say it. This list shows which parts you can explain out loud and which need another look.
🧠 Check your understanding
1
In your own words, explain why a doula's non-clinical status is called a strength and not a limit. What can a doula do that no clinical provider can?
2
Research shows nurses spend only 6–10% of their time on direct labor support. Why does this gap exist? How does knowing this help you work well with nurses?
3
The Falconi et al. (2022) study found the strongest results when doulas worked alongside midwife-led teams. What does this say about how doula support and medical care fit together?
4
A client's OB-GYN suggests something your client did not expect. Walk through how you would support her in that moment. Be specific about what you would do and what you would not do.
Peer-reviewed references
- Bohren, M. A., Hofmeyr, G. J., Sakala, C., Fukuzawa, R. K., & Cuthbert, A. (2017). Continuous support for women during childbirth. Cochrane Database of Systematic Reviews, 7, CD003766. https://doi.org/10.1002/14651858.CD003766.pub6
- Falconi, A. M., Bromfield, S. G., Tang, T., & Disciglio, R. (2022). Doula care across the maternity care continuum and impact on maternal health: Evaluation of doula programs across three states using propensity score matching. eClinicalMedicine (The Lancet), 50, 101531. https://doi.org/10.1016/j.eclinm.2022.101531
- McLeish, J., & Redshaw, M. (2018). A qualitative study of volunteer doulas working alongside midwives at births in England: Mothers' and doulas' experiences. Midwifery, 56, 53–60. https://doi.org/10.1016/j.midw.2017.10.002
- Wójcik-Brylska, K., Pawlicka, P., Tataj-Puzyna, U., Szlendak, B., Węgrzynowska, M., Pięta, B., & Baranowska, B. (2023). Cooperation between midwives and doulas in the context of perinatal care: An integrative review. Midwifery, 124, 103731. https://doi.org/10.1016/j.midw.2023.103731
- Al-Adeli, N., et al. (2025). Role of doulas across the pregnancy care continuum on maternal and child health: A scoping review. npj Women's Health. https://doi.org/10.1038/s44294-025-00109-4
- Exploring innovative models of doula services in maternity care: A qualitative study on advancing equity and addressing disparities. (2024). PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC12144344/
- Tumblin, A., & Simkin, P. (2001). Pregnant women's perceptions of their nurse's role during labor and delivery. Birth, 28(1), 52–56. [Referenced via Al-Adeli et al., 2025 — nurses spend only 6–10% of time on labor support vs. 53% expected by patients]
Featured Study

Falconi, A. M., & colleagues (2022). Doula Care Across the Maternity Care Continuum.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC9257331/
Summary:
This research evaluated doula programs across three U.S. states, focusing on maternal health outcomes using matched comparison methods. It found that women with doulas had lower odds of cesarean section and lower likelihood of postpartum depression or anxiety. The magnitude of these effects varied depending on the timing of support. The study also suggests doulas may help reduce disparities in outcomes for socioeconomically vulnerable and marginalized groups. It noted comprehensive evidence that doula involvement relates to improved maternal health, although more research is needed. Strengths of the study included reducing selection bias by using claim data and matched comparisons.
What It Means to Birth Doulas:
This study reinforces that doula care may improve both physical outcomes (like fewer cesareans) and emotional well-being after birth. It also underscores the importance of when doulas engage in care (early prenatal vs. only during labor). For doulas, this supports intentional integration of emotional support skills alongside physical comfort strategies. The findings also emphasize the role of doulas in health equity by supporting marginalized groups. It encourages doulas to document their impact and contribute to broader maternal health conversations.
Translating for Clients:
Use evidence to normalize the value of emotional support:
“Studies show that women with doulas had lower rates of cesarean birth and lower risk of anxiety or depression after birth.”
Help them connect expectations with care:
“Talking about your feelings and comfort needs early can make a real difference — and that’s part of what I’m here to support.”
Highlight continuity:
“We’ll work together from pregnancy through early postpartum so you feel supported at every stage.”
Module 1: Introduction to Birth Doula Work
Lesson 1.1 Quiz: What Is a Birth Doula?
Test your understanding of what a birth doula is, the history of doula work, and how doulas differ from midwives and other birth professionals. Select an answer for each question to see immediate feedback.
1. What is a birth doula?
✓ Correct! A birth doula is a trained, non-medical support person. The role is centered on continuous physical, emotional, and informational support — not clinical care.
✗ Not quite. Birth doulas are not medical professionals. They are trained companions who provide non-medical support throughout the childbirth journey.
2. Where does the word "doula" originate from?
✓ Correct! The word "doula" comes from ancient Greek, meaning "a woman who serves." It reflects the long tradition of women supporting other women through birth.
✗ Not quite. The term "doula" has Greek origins, meaning "a woman who serves" — pointing to the role's deep historical roots in serving birthing people.
3. Which of the following best describes the historical role of doulas across cultures?
✓ Correct! Women supporting other women in childbirth is one of the oldest traditions in human history, found across cultures worldwide — long before the modern doula movement was named.
✗ Not quite. Doula-like support has existed for centuries across many cultures — it is not a modern invention or limited to one region.
4. The modern doula movement, as we know it today, gained traction primarily in which decade?
✓ Correct! The modern doula movement took shape between the 1970s and 1990s, with research and formal training organizations developing during this period.
✗ Not quite. While doula-like roles existed for centuries, the modern doula movement and formal training programs emerged in the late 20th century.
5. What is the main difference between a birth doula and a midwife?
✓ Correct! This is the core distinction: midwives are medical care providers who can deliver babies and manage clinical care, while doulas offer non-medical, continuous support.
✗ Not quite. The key difference is scope: midwives are trained medical professionals, while doulas provide non-medical support.
6. Which of the following is NOT a role of a birth doula?
✓ Correct! Vaginal exams and fetal monitoring are clinical tasks performed by medical professionals — not doulas. Doulas stay within a non-medical support role.
✗ This is actually a valid doula role. Look for the option involving clinical or medical tasks — that's the one outside a doula's scope.
7. How does a birth doula typically work alongside a doctor or midwife?
✓ Correct! Doulas don't replace medical providers — they work alongside them, filling the gap with continuous emotional, physical, and informational support.
✗ Not quite. Doulas complement, rather than replace, clinical care. Their role is to support the birthing person while the medical team handles the clinical side.
8. True or False: A birth doula provides medical advice and clinical recommendations.
✓ Correct! Doulas do not give medical advice. They share information and resources, but clinical recommendations come from medical providers.
✗ Actually, false. Doulas may share information, but they do not give medical advice or make clinical recommendations — that's the role of doctors and midwives.
9. Which of the following best describes the type of support a doula provides?
✓ Correct! Doulas are known for their three-pronged support: physical (comfort measures), emotional (reassurance and presence), and informational (helping clients understand options).
✗ Not quite. The hallmark of doula support is its three-part nature: physical, emotional, and informational — all non-medical.
10. Which statement best summarizes what a birth doula is?
✓ Correct! That's the heart of birth doula work — trained, non-medical, continuous support that walks alongside the birthing person and their family before, during, and after birth.
✗ Not quite. A birth doula is trained (not untrained), non-medical (not clinical), and offers continuous support throughout pregnancy, birth, and postpartum.
-
A birth doula is a trained professional who provides continuous physical, emotional, and informational support to a birthing person before, during, and shortly after childbirth.
Doulas do not provide medical care but work alongside healthcare providers to enhance the birth experience.
-
Bohren, M. A., Hofmeyr, G. J., Sakala, C., Fukuzawa, R. K., & Cuthbert, A. (2017). Continuous support for women during childbirth. Cochrane Database of Systematic Reviews, 7, CD003766. https://doi.org/10.1002/14651858.CD003766.pub6
This Cochrane Review found that continuous labor support, often provided by doulas, leads to shorter labors, fewer cesareans, less need for pain medication, and greater maternal satisfaction.Steel, A., Frawley, J., Sibbritt, D., & Adams, J. (2015). Trained or professional doulas in the support and care of pregnant and birthing women: A critical integrative review. Health & Social Care in the Community, 23(3), 225–241. https://doi.org/10.1111/hsc.12112
This review examined professionalization of doulas, highlighting their unique role distinct from midwives and physicians, and how role clarity influences care experiences.McLeish, J., & Redshaw, M. (2018). A qualitative study of volunteer doulas working alongside midwives at births in England: Mothers’ and doulas’ experiences. BMC Pregnancy and Childbirth, 18, 35. https://doi.org/10.1186/s12884-018-1667-0
This study found that respectful collaboration between doulas and midwives improved women’s experiences, reduced stress, and enhanced communication in maternity care.Jordan, B. (1993).Birth in four cultures: A crosscultural investigation of childbirth in Yucatan, Holland, Sweden, and the United States (4th ed.). Prospect Heights, IL: Waveland Press.
Jordan’s anthropological work documents that birth support figures are a cross-cultural constant, embedding the doula role in human societies historically.Kennell, J. H., Klaus, M. H., McGrath, S. K., Robertson, S., & Hinkley, C. (1991). Continuous emotional support during labor in a US hospital: A randomized controlled trial. JAMA, 265(17), 2197–2201. https://doi.org/10.1001/jama.1991.03460170051032
This landmark RCT showed that continuous emotional support shortened labor, lowered cesarean rates, and reduced need for pain relief, sparking modern doula interest.Kozhimannil, K. B., Hardeman, R. R., Attanasio, L. B., Blauer-Peterson, C., & O’Brien, M. (2016). Doula care, birth outcomes, and costs among Medicaid beneficiaries. American Journal of Public Health, 106(4), 698–704. https://doi.org/10.2105/AJPH.2015.302982
This study found that Medicaid beneficiaries with doula support had lower odds of cesarean delivery, lower costs, and improved maternal satisfaction, especially among women of color.Gruber, K. J., Cupito, S. H., & Dobson, C. F. (2013). Impact of doulas on healthy birth outcomes. Journal of Perinatal Education, 22(1), 49–58. https://doi.org/10.1891/1058-1243.22.1.49
This study reported that doula care was associated with reduced anxiety, fewer symptoms of postpartum depression, and healthier maternal mental health. -
Falconi, A. M., Ramirez, L., & Levin, C. (2024). Role of doulas in improving maternal health and health equity among Medicaid enrollees, 2014–2023. 114(11):1275–1285. https://doi.org/10.2105/AJPH.2024.307805
Lay Summary:
This large U.S. study analyzed health insurance claims data comparing people with doula services to those without. It found 47% lower risk of cesarean delivery and 29% lower risk of preterm birth among those with doulas. Clients supported by doulas were also 46% more likely to attend postpartum checkups. These outcomes suggest doulas contribute to both physical health and healthcare engagement after birth. The research included matched pairs of Medicaid enrollees, meaning groups were comparable on key demographics. The study supports doulas as a strategy to reduce disparities in maternal health. It also noted the growing policy interest in dolua coverage.What It Means to Birth Doulas:
This evidence is powerful for doulas working with marginalized or low-income clients. It affirms that doula care is linked to significant reductions in common risks like cesareans and preterm birth. The increased likelihood of postpartum visits suggests doulas support holistic care continuity, not only during labor. For doulas, it’s a reminder to emphasize coordination with clinical teams. It also supports advocacy for broader doula access and insurance coverage. This study strengthens the argument that doulas contribute to health equity.Translating for Clients:
In consultations, you might say:“Research found that people with doula support had almost half the risk of cesarean delivery and had healthier timing of birth.”
Frame postpartum care as part of holistic support:
“People with doulas were more likely to go to their postpartum check-ups — that’s important for long-term health.”
This ties into empowerment and advocacy. Link evidence to their goals, e.g., “Let’s discuss how your preferences for birth and early support can shape your care plan.”